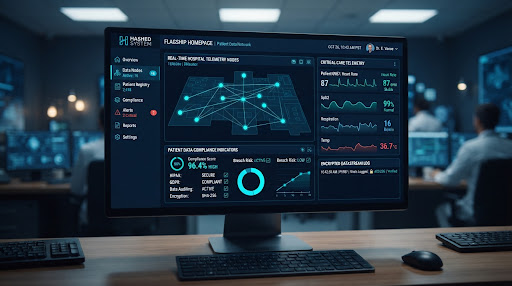
Healthcare software development has one unforgiving characteristic: compliance isn’t a feature you add before launch, it’s a set of architectural constraints that shape the entire system. Teams that treat HIPAA and GDPR as a pre-launch checklist consistently end up rebuilding core parts of their data architecture — an expensive lesson learned too late.
(This post covers general architectural principles. Confirm specific compliance requirements with qualified legal counsel, as healthcare regulations are detailed and vary by jurisdiction and use case.)
Why This Has to Start at the Architecture Stage
HIPAA and GDPR both fundamentally shape how patient/health data can be collected, stored, accessed, and shared. This affects:
- Your data model — what health information you collect, and whether it needs to be segmented from other data
- Access control design — who and what systems can access protected health information, and how that’s enforced technically, not just by policy
- Data storage decisions — encryption requirements, and for GDPR, potentially data residency considerations
- Third-party integrations — every vendor touching patient data (analytics, cloud hosting, AI services) needs to meet the same compliance bar, which affects which tools and services you can even use
Retrofitting these constraints into a system built without them in mind is typically a significant re-architecture, not a patch.
Core HIPAA Technical Requirements
Access controls. Role-based access ensuring only authorized personnel and systems can access Protected Health Information (PHI), with unique user identification and automatic session timeouts.
Audit controls. Detailed logging of who accessed what PHI, when, and what they did with it — a technical requirement, not just a policy statement, and one that needs to be built into the system from the start.
Encryption. PHI needs encryption both at rest and in transit, using recognized encryption standards.
Data integrity controls. Mechanisms to ensure PHI isn’t improperly altered or destroyed, including backup and disaster recovery processes.
Business Associate Agreements (BAAs). Any third-party vendor that touches PHI on your behalf (cloud hosting, analytics, AI providers) needs a BAA in place — and critically, not every vendor will sign one, which directly constrains which tools and services you can architect your system around.
Core GDPR Requirements Relevant to Healthcare Apps
Lawful basis for processing. Health data is a “special category” under GDPR requiring a specific lawful basis (often explicit consent) beyond what’s needed for typical personal data.
Data minimization. Collecting only the health data genuinely necessary for the app’s function — a principle that should shape your data model from the design stage, not just your privacy policy.
Right to erasure and data portability. Users can request deletion or export of their data, which requires your data architecture to actually support locating and extracting/deleting a specific user’s data across all systems, including backups and any AI or analytics pipelines that processed it.
Data Protection Impact Assessments (DPIAs). Processing health data at scale typically requires a formal DPIA before launch — a process worth starting early, since it can surface architectural changes needed before development is far along.
Architectural Decisions That Save Rework Later
Segment PHI from other application data. Keeping health data in a clearly bounded part of your system, with its own stricter access controls, makes compliance auditing and access control enforcement significantly cleaner than health data scattered throughout a general application database.
Choose infrastructure providers that support compliance from the start. Major cloud providers offer HIPAA-eligible services and will sign BAAs, but only for specific services within their platform — using a non-eligible service for PHI, even accidentally, creates a compliance gap. This needs to be verified explicitly, not assumed.
Build audit logging in from day one. Retrofitting comprehensive audit logs into an already-built system, especially one with data flowing through multiple services, is significantly more work than designing it in from the start.
Be deliberate about AI features. If your app uses AI for triage, diagnostics support, or any function touching PHI, verify that your AI provider will sign a BAA and that PHI isn’t inadvertently used for model training in a way that violates your compliance obligations. Not all AI providers support this by default — this needs explicit verification, not assumption.
Plan for data subject requests as a system capability. Both HIPAA and GDPR create obligations around data access requests. Building this as a supported system function, rather than a manual engineering task performed each time a request comes in, saves significant operational cost down the line.
Common Compliance Mistakes in Healthcare App Development
- Assuming a “HIPAA compliant” cloud provider makes the whole app automatically compliant — compliance depends on how each specific service is configured and used, not just the provider’s general certification
- Treating consent as a one-time checkbox rather than a system that can track, enforce, and support withdrawal of specific consents
- Underestimating third-party vendor risk — every vendor touching PHI needs to be vetted for compliance, including analytics tools that might seem unrelated to health data
- Delaying compliance review until pre-launch, when architectural changes are far more expensive to make
The Bottom Line
Healthcare software development done well treats HIPAA and GDPR requirements as architectural inputs from the very first design decisions — not a compliance review squeezed in before launch. The technical requirements (access control, audit logging, encryption, vendor management) are substantial, but far more manageable when built in from the start than when retrofitted into a system that wasn’t designed with them in mind. Given the complexity and the real legal stakes, working with a development partner who has actual delivered experience in healthcare-compliant systems — not just familiarity with the acronyms — is worth the investment.
Principal Solutions Architect at Hashed System DIFC. Former systems researcher at Stanford Cryptography Group. Specializes in verifiable computation, enclave attestation, and sovereign digital infrastructures across the GCC.